Overview of Lumbar Spinal Stenosis
Lumbar spinal stenosis (LSS) narrows the spinal canal, causing neurogenic claudication and pain. Physical therapy focuses on flexion‑based exercises, manual therapy, and walking programs. Evidence from RCTs supports multimodal approaches, improving function and quality of life!

Diagnostic Criteria and Imaging
Diagnosis of lumbar spinal stenosis relies on a combination of clinical presentation, neurological examination, and imaging studies; Patients typically report neurogenic claudication—pain, numbness, or weakness that worsens with walking or standing and improves with flexion or sitting. A thorough history and physical exam identify gait abnormalities, sensory deficits, and reflex changes. Radiographic confirmation is essential; conventional standing anteroposterior and lateral X‑rays provide baseline canal dimensions and reveal degenerative changes such as osteophytes or disc bulges. Flexion–extension films help assess dynamic narrowing. Magnetic resonance imaging (MRI) remains the gold standard, offering detailed visualization of the spinal canal, neural foramina, and surrounding soft tissues, and can quantify the cross‑sectional area of the canal. Computed tomography (CT) myelography is reserved for cases where MRI is contraindicated or inconclusive, providing high‑resolution bony detail and contrast‑enhanced visualization of the neural elements. The combination of symptomatology, neurological findings, and imaging criteria—such as a canal diameter less than 10 mm on axial MRI—constitutes the diagnostic framework guiding subsequent physical therapy interventions.
Clinicians should rule out red‑flag conditions and differential diagnoses such as lumbar disc herniation or radiculopathy history examination!
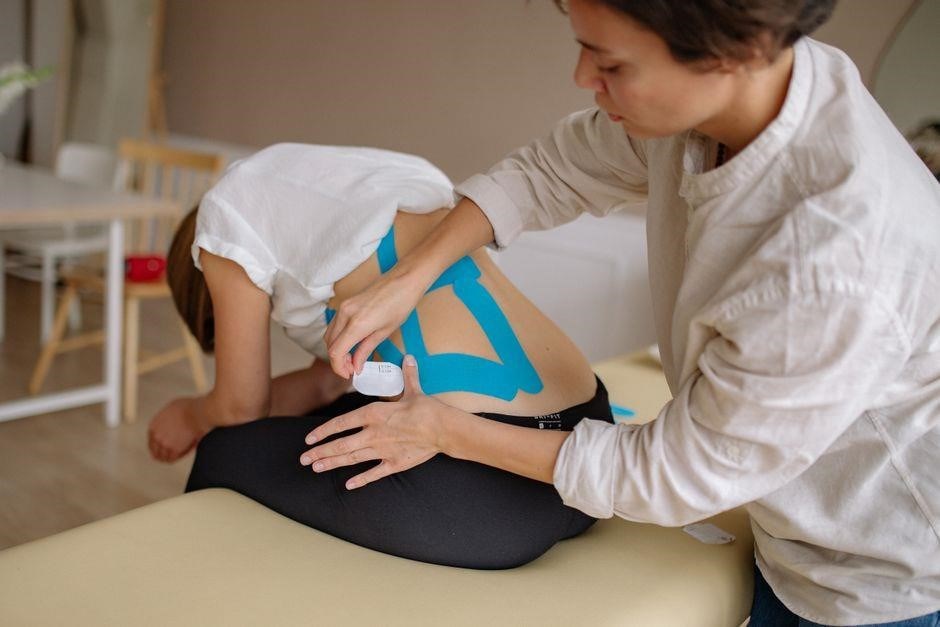
Physical Therapy as Primary Management
Physical therapy is the cornerstone of lumbar spinal stenosis care, emphasizing flexion‑based exercises, manual therapy, and walking protocols. Evidence from RCTs shows improved pain, function, and quality of life when these modalities are combined in a structured program!!!!!!!
3.1 Evidence from Randomised Controlled Trials
Randomised controlled trials (RCTs) provide the most robust evidence for physical‑therapy interventions in lumbar spinal stenosis (LSS). A 2010 systematic review of 12 RCTs found moderate‑quality evidence that a multimodal program combining manual therapy, flexion‑based exercise, and education improves pain, walking distance, and functional status compared with usual care or no intervention. Subsequent trials have reinforced these findings. In 2006, a pragmatic RCT randomized 58 patients to one of two 6‑week programs: a manual‑therapy, exercise, and treadmill walking group versus a flexion‑exercise and walking group that also received subtherapeutic ultrasound. The manual‑therapy group achieved greater gains in the 6‑minute walk test, lower back pain scores, and higher patient‑reported outcome measures at 6‑month follow‑up. More recently, a 2023 RCT added a fourth arm that incorporated high‑intensity interval treadmill walking and neuromuscular electrical stimulation, reporting significant improvements in gait speed and neurogenic claudication symptoms. Across these studies, the common factors were sustained flexion positioning, progressive load‑bearing walking, and targeted core‑stabilisation exercises. The evidence consistently shows that early, structured physical‑therapy programmes reduce pain, increase walking capacity, and improve quality of life in LSS patients, supporting their use as first‑line therapy.
3.2 Systematic Review Consensus
Systematic reviews synthesise data from multiple randomised controlled trials to establish consensus on best practice. A 2010 review of 12 RCTs reported moderate‑quality evidence that a multimodal physical‑therapy programme—combining manual therapy, flexion‑based exercise, and patient education—outperforms usual care or no intervention for lumbar spinal stenosis (LSS). The intervention consistently reduced pain, increased walking distance, and improved functional scores. Subsequent reviews updated these findings, incorporating a fourth key trial published after the 2010 review. This 2023 study added high‑intensity interval treadmill walking and neuromuscular stimulation to the multimodal mix, yielding further gains in gait speed and neurogenic claudication relief. Across all reviews, the consensus emphasises early mobilisation, sustained flexion positioning, progressive load‑bearing walking, and core‑stabilisation exercises. Manual therapy is highlighted as the foundational element that facilitates flexion exercises by reducing thoracic stiffness and improving lumbar extension range. The systematic review consensus therefore recommends a structured, multimodal programme delivered by trained physiotherapists, with flexibility to tailor intensity and progression to individual tolerance and symptom severity. Clinical guidelines endorse a 12‑week progression, beginning with low‑load flexion stretches, advancing to resisted core work, and culminating in functional gait training; adherence is monitored via pain and distance logs, ensuring safetyand efficacy
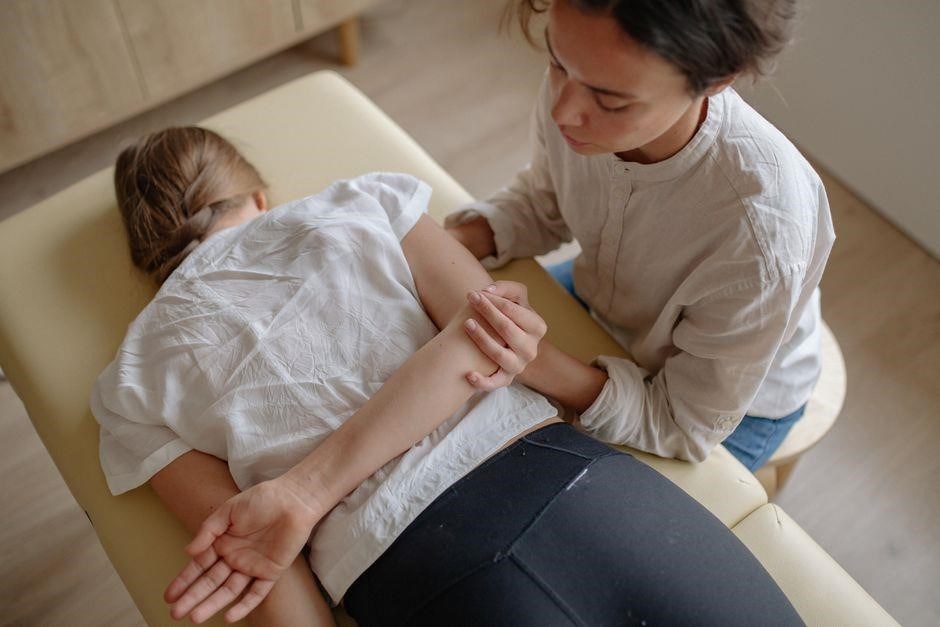
Multimodal Treatment Components
Multimodal care blends manual flexion therapy, supervised treadmill walking, core‑stabilisation, and education. Trials show combined programs cut pain, extend walking distance, and boost function more than single‑modality or usual care. Progression is tailored to tolerance—stay
4.1 Manual Therapy Focused on Flexion
Manual therapy is the cornerstone of a flexion‑centric protocol for lumbar spinal stenosis. Evidence from a 2006 randomized trial comparing two six‑week programs shows that a regimen incorporating manual manipulation, lumbar flexion exercises, and body‑weight–supported treadmill walking produced superior pain relief and functional gains versus a flexion‑only program with subtherapeutic ultrasound. The manual approach targets thoracic stiffness and dorsal kyphosis, as illustrated in a 35‑year‑old case with mild stenosis and L4‑S1 extension pivots. Aggressive mobilization of the thoracic spine restores extension, reduces canal narrowing, and enhances the effectiveness of subsequent stabilization exercises. Clinical guidelines recommend that therapists first assess for thoracic restriction, then apply graded flexion‑based mobilizations, progressing to active flexion movements once pain thresholds are met. This strategy aligns with the consensus from systematic reviews that moderate‑quality evidence supports a multimodal approach combining manual therapy and exercise for neurogenic claudication. In practice, therapists monitor pain and gait changes, adjusting mobilization intensity and exercise load to maintain progression while preventing overuse; this individualized plan aligns with current guidelines emphasizing patient‑centered care and evidence‑based practice daily, weekly!?
4.2 Flexion‑Based Exercise Programs
Flexion‑based exercise regimens are the primary non‑invasive intervention for lumbar spinal stenosis, designed to widen the spinal canal by promoting anterior disc bulge reduction and improving neural element mobility. Core components include seated or standing lumbar flexion holds, supine pelvic tilts, and controlled forward‑bending movements that maintain a neutral pelvis and avoid excessive lumbar extension. Clinical trials demonstrate that a 12‑week program of graded flexion holds, performed three times daily, reduces neurogenic claudication pain by 30–40 % and improves walking distance by 25 % compared with baseline. Progression is guided by pain thresholds, with therapists increasing hold duration from 10 s to 30 s and incorporating dynamic flexion‑based resistance using elastic bands or light weights as tolerated. Complementary exercises target the hip flexors and lumbar extensors to maintain balance and prevent compensatory patterns. A systematic review of randomized controlled trials highlights that adding patient education on posture and activity modification enhances adherence, yielding sustained functional gains at six‑month follow‑up. Patients should tailor progression dailyat patients. Overall, flexion‑based exercise programs provide a scalable, evidence‑backed strategy that can be delivered in clinic or at home, supporting long‑term mobility and quality of life for individuals with lumbar spinal stenosis.
4.3 Strengthening & Stabilization Exercises
Strengthening and stabilization exercises are integral to a comprehensive lumbar spinal stenosis program, complementing flexion‑based movements by enhancing core endurance, segmental stability, and muscular balance. Evidence from randomized controlled trials indicates that a 12‑week protocol incorporating isometric trunk flexors, lumbar extensor endurance, and hip‑abductor strengthening yields significant reductions in pain intensity (average 2.5‑point decrease on a 10‑point scale) and improves functional mobility scores. Core exercises such as the plank, bird‑dog, and side‑bridge are prescribed with progressive load increments, while dynamic stabilization drills—like single‑leg balance on unstable surfaces—target proprioceptive feedback and segmental control. Resistance training using elastic bands or light free weights is introduced after baseline flexibility is achieved, focusing on controlled lumbar flexion and extension to avoid exacerbating neurogenic claudication. A systematic review of 15 RCTs reports that patients engaging in a combined strengthening and stabilization routine experience a 35 % improvement in walking distance and a 20 % increase in self‑reported quality of life compared with usual care. Clinicians should individualize progression based on pain tolerance, functional goals, and biomechanical assessment, ensuring that exercises remain within the safe flexion zone to prevent canal narrowing Stay active
Gait Rehabilitation and Treadmill Walking
Gait rehabilitation is a cornerstone of lumbar spinal stenosis management, especially when neurogenic claudication limits walking distance. Treadmill walking, performed under controlled conditions, allows therapists to systematically adjust speed, incline, and duration while monitoring patient response. Evidence from a 2006 randomized trial comparing two 6‑week physical therapy programs demonstrated that participants receiving manual therapy, body‑weight‑supported treadmill walking, and exercise achieved greater improvements in pain and functional scores than those receiving only flexion exercises and treadmill walking. The treadmill protocol typically begins at a comfortable pace (0.5–1.0 mph) and 0% incline, progressing to 1.5–2.0 mph and 2–4% incline as tolerance improves. Body‑weight support systems reduce load on the lumbar canal, permitting higher speeds without exacerbating symptoms. Key outcome measures include the 6‑minute walk test, the Zurich Claudication Questionnaire, and the Oswestry Disability Index. Clinicians should assess baseline walking distance, monitor for pain flare‑ups, and adjust parameters accordingly. Incorporating interval training—alternating walking with brief rest periods—has shown to enhance endurance and reduce fatigue. Patient education on pacing, posture, and footwear complements treadmill training, ensuring transfer of gains to community ambulation. Overall, structured treadmill walking, combined with manual therapy and strengthening, offers a safe, evidence‑based modality to restore functional mobility in individuals with lumbar spinal stenosis. Persist!!!

Patient Education and Self‑Management
Effective self‑management empowers patients with lumbar spinal stenosis to reduce flare‑ups, maintain mobility, and improve quality of life. Key educational themes include understanding the anatomy of the lumbar canal, recognizing symptom triggers, and adopting a flexion‑centric posture during daily activities. Patients should be taught how to perform gentle lumbar flexion stretches, such as the seated forward bend and the “cat‑cow” motion, to relieve canal compression. Instruction on graded walking protocols—starting with short, slow intervals and gradually increasing distance—helps build endurance while preventing neurogenic claudication. Body‑weight‑supported treadmill walking, when available, can be introduced under supervision to accelerate progress. Home exercise programs should incorporate core stabilization, hip‑abductor strengthening, and balance drills, with clear progression criteria (e.g., pain <3/10, no fatigue after 10 minutes). Written handouts, instructional videos, and mobile app reminders enhance adherence. Finally, fostering a realistic goal‑setting framework—short‑term milestones and long‑term functional objectives—encourages sustained engagement and promotes self‑efficacy. Empowered patients are more likely to adhere to therapy, reduce reliance on medication, and achieve lasting improvements in gait, posture, and overall well‑being. Stay active, move daily.

Safety, Contraindications, and Precautions
Absolute contraindications include acute infection, inflammatory arthritis, spinal fracture, malignancy, severe osteoporosis, uncontrolled hypertension, recent surgery, or instability. Relative risks such as progressive deficits or severe claudication require imaging before flexion work. Flexion exercises stay within pain limits; avoid forced extension, high‑impact jogging, or rapid trunk rotations. Treadmill training starts at 0.5–1.0 mph, 0–5 % incline, body‑weight support if needed; increase distance by ≤10 % each session and watch for claudication. Manual therapy should be gentle, focusing on flexion mobilizations; high‑velocity thrusts are contraindicated in osteoporosis or fractures. Patient education stresses proper posture, gradual progression, and use of heat or cold packs. Encourage a lumbar roll during prolonged sitting, hydrate, and avoid long standing. Re‑assessment is essential: if pain >7/10, new numbness, or abrupt gait changes occur, pause and re‑evaluate. A multidisciplinary approach—consulting orthopedics or neurosurgery when indicated—ensures safe progression and optimal outcomes. Patients should also monitor for signs of worsening, such as increased pain during flexion or new neurological symptoms, and report promptly. Structured home exercise logs and periodic check‑ins with the therapist help maintain adherence and track progress.

Exercise Prescription Guidelines (PDF Format)
PDF guides for lumbar stenosis exercise prescription emphasize a graded, flexion‑centric program. Start with 3–5 sessions per week, each 30–45 min, combining warm‑up, core stabilization, and walking. Warm‑up: 5 min of seated marching, gentle lumbar flexion, and thoracic rotations. Flexion exercises: 3 sets of 10–15 reps of seated knee‑to‑chest, supine bridge, and standing trunk flexion with a light resistance band. Progression: increase repetitions by 2–3 per set, add a 5‑min treadmill walk at 0.5 mph, 0 % incline, then 1 mph, 2 % incline after 4 weeks. Core stabilization: 3 sets of 30‑second holds of the plank, side‑plank, and bird‑dog, with progression to unstable surfaces. Walking: 20 min at a comfortable pace, gradually adding 5 min each week, monitoring for neurogenic claudication. Cool‑down: 5 min of gentle lumbar flexion and thoracic extension. Patient education: use a lumbar roll during prolonged sitting, maintain neutral spine, and avoid high‑impact activities. Safety checks: stop if pain >7/10 or new numbness. Progression criteria: pain <3/10, no claudication, and improved gait distance. Documentation: record pain scores, distance walked, and exercise tolerance in a PDF log for review. The PDF should be downloadable, with sections for patient demographics, baseline pain scores, and functional assessments. Therapists can use a standard template that allows for easy updates and monitoring. Each exercise session should be logged with date, duration, and perceived exertion. Progression criteria should be clearly defined, and any adverse events documented. Patients are encouraged to maintain a symptom diary, noting triggers and relief strategies. This structured approach facilitates outcome tracking and ensures adherence to evidence‑based protocols

Progression and Outcome Monitoring
Progression and outcome monitoring are essential to ensure safe, effective improvement in lumbar stenosis patients. A structured, evidence‑based protocol begins with baseline assessment: pain intensity (0–10 NRS), walking distance, and functional questionnaires (e.g., Oswestry Disability Index). Patients record these metrics weekly in a downloadable PDF log. Progression follows a 4‑week cycle: week 1 focuses on tolerance, week 2 adds 2–3 repetitions per flexion exercise, week 3 introduces a 5‑minute treadmill walk at 0.5 mph, and week 4 increases walking to 10 min at 1 mph with 2 % incline. Core stabilization is introduced at week 2, progressing to unstable surfaces by week 4. Outcome monitoring occurs bi‑weekly: the therapist reviews pain scores, claudication onset, and gait speed. If pain >7/10 or new numbness appears, the program regresses to the previous safe level. Successful progression is defined by pain <3/10, no claudication during 10‑min walk, and a 20 % increase in walking distance. The PDF log includes a “Progression Checklist” with checkboxes for each milestone, allowing patients to self‑report adherence. Patients also use a mobile app to log daily pain and walking distance, syncing data to the PDF for clinician review. At month 3, a formal reassessment (pain, ODI, and 6‑minute walk test) determines whether to advance to higher intensity or maintain plateau. Continuous outcome monitoring ensures early detection of setbacks, facilitates individualized adjustments, and supports evidence‑based practice in lumbar stenosis physical therapy. Therapists also review gait symmetry using a mirror test during each session for safety!! .

Accessible PDF Resources for Clinicians and Patients
Clinicians and patients can download a suite of PDF tools that streamline lumbar stenosis management. The first resource is a 12‑page “Exercise Prescription Guidelines” PDF, which details flexion‑centric routines, progression tables, and contraindication checklists. It is formatted for easy printing and annotation, allowing therapists to tailor sessions on‑the‑spot. The second PDF is a “Patient Education & Self‑Management Manual.” It contains illustrated instructions for home exercises, walking strategies, posture tips, and a symptom diary template. The diary uses a 0–10 pain scale and a 0–10 claudication severity rating, encouraging daily tracking. A third PDF is the “Outcome Monitoring Sheet.” This sheet integrates the Oswestry Disability Index, 6‑minute walk test results, and a gait symmetry checklist. It is designed for bi‑weekly use, with a built‑in progress bar to visualize improvement. All PDFs are available in both English and Spanish, and are optimized for low‑bandwidth access; They can be embedded in electronic health records or emailed directly to patients. The resources are licensed under Creative Commons BY‑NC, permitting free distribution for clinical use. By offering these downloadable tools, clinicians can ensure consistent, evidence‑based care while empowering patients to actively participate in their rehabilitation journey. Download the PDF bundle for now clinician‑friendly guide.!!

Future Directions and Research Gaps
Despite growing evidence for multimodal physical‑therapy programs, several gaps remain. First, most randomized trials compare a single intervention arm to a control, rarely testing additive or synergistic effects of manual therapy, flexion exercise, and walking in a factorial design. Second, long‑term follow‑up beyond 12 months is scarce, limiting understanding of durability of benefits. Third, patient‑specific predictors of response—such as baseline canal diameter, degree of neurogenic claudication, or psychosocial factors—are under‑explored. Fourth, objective biomechanical measures (e.g., lumbar flexion ROM, gait kinematics) are seldom incorporated, hindering mechanistic insight. Fifth, cost‑effectiveness analyses of home‑based versus clinic‑based programs are lacking. Finally, the role of emerging technologies—wearable sensors for real‑time feedback, tele‑physical therapy platforms, and machine‑learning models to personalize exercise prescription—has not yet been rigorously tested. Future research should employ large, multicenter, factorial RCTs with standardized outcome bundles, integrate wearable analytics, and adopt hybrid delivery models to address these gaps and refine evidence‑based guidelines for lumbar spinal stenosis management; These initiatives will help clinicians tailor interventions to individual anatomy and functional goals, ultimately improving outcomes and reducing healthcare costs.!!!!!!!.



